Pheochromocytoma is a catecholamine-secreting tumor derived from chromaffin cells. The majority of tumors originate in the adrenal medulla, but they may also arise from sympathetic ganglia (also referred to as paraganglioma). Symptoms are associated with excessive catecholamine production and commonly include hypertension, tachycardia, headache, and sweating. Pheochromocytomas are frequently familial and associated with genetic syndromes. Approximately 90% of pheochromocytomas are benign and surgical resection is the only curative treatment. Prognosis is generally good for benign, sporadic tumors that have been completely resected. Familial forms are associated with higher recurrence rates and malignant potential.
PheochromocytomaPheochromocytomaPheochromocytoma is a catecholamine-secreting tumor derived from chromaffin cells. The majority of tumors originate in the adrenal medulla, but they may also arise from sympathetic ganglia (also referred to as paraganglioma). Symptoms are associated with excessive catecholamine production and commonly include hypertension, tachycardia, headache, and sweating. Pheochromocytomais a catecholamine-secreting tumorTumorInflammation derived from chromaffin cellsChromaffin cellsCells that store epinephrine secretory vesicles. During times of stress, the nervous system signals the vesicles to secrete their hormonal content. Their name derives from their ability to stain a brownish color with chromic salts. Characteristically, they are located in the adrenal medulla and paraganglia of the sympathetic nervous system.Adrenal Hormones.
Anatomy[4]
Pheochromocytomas and paragangliomas (PPGL)
80–85% located in adrenal glands
Familial cases tend to be bilateral.
PheochromocytomaPheochromocytomaPheochromocytoma is a catecholamine-secreting tumor derived from chromaffin cells. The majority of tumors originate in the adrenal medulla, but they may also arise from sympathetic ganglia (also referred to as paraganglioma). Symptoms are associated with excessive catecholamine production and commonly include hypertension, tachycardia, headache, and sweating. Pheochromocytoma (PCC) arises from the adrenal medullaAdrenal MedullaThe inner portion of the adrenal gland. Derived from ectoderm, adrenal medulla consists mainly of chromaffin cells that produces and stores a number of neurotransmitters, mainly adrenaline (epinephrine) and norepinephrine. The activity of the adrenal medulla is regulated by the sympathetic nervous system.Adrenal Glands: Anatomy.
ParagangliomaParagangliomaA neural crest tumor usually derived from the chromoreceptor tissue of a paraganglion, such as the carotid body, or medulla of the adrenal gland (usually called a chromaffinoma or pheochromocytoma). It is more common in women than in men.Hearing Loss(PGL) is extra-adrenal pheochromocytomaExtra-Adrenal PheochromocytomaPheochromocytoma:
Develops in paraganglion chromaffin tissue of sympathetic ganglia
Anywhere from base of brainBrainThe part of central nervous system that is contained within the skull (cranium). Arising from the neural tube, the embryonic brain is comprised of three major parts including prosencephalon (the forebrain); mesencephalon (the midbrain); and rhombencephalon (the hindbrain). The developed brain consists of cerebrum; cerebellum; and other structures in the brain stem.Nervous System: Anatomy, Structure, and Classification to urinary bladderUrinary BladderA musculomembranous sac along the urinary tract. Urine flows from the kidneys into the bladder via the ureters (ureter), and is held there until urination.Urinary Tract: Anatomy
By location:
Sympathetic (typically catecholamine-secreting): extra-adrenal sympathetic paraganglia in the abdomen, pelvisPelvisThe pelvis consists of the bony pelvic girdle, the muscular and ligamentous pelvic floor, and the pelvic cavity, which contains viscera, vessels, and multiple nerves and muscles. The pelvic girdle, composed of 2 “hip” bones and the sacrum, is a ring-like bony structure of the axial skeleton that links the vertebral column with the lower extremities.Pelvis: Anatomy, or thorax which are
Urinary bladderUrinary BladderA musculomembranous sac along the urinary tract. Urine flows from the kidneys into the bladder via the ureters (ureter), and is held there until urination.Urinary Tract: Anatomy
Parasympathetic (usually non-secretory, <5% functional): predominantly in the head and neckNeckThe part of a human or animal body connecting the head to the rest of the body.Peritonsillar Abscess which are:
Carotid bodyCarotid bodyA small cluster of chemoreceptive and supporting cells located near the bifurcation of the internal carotid artery. The carotid body, which is richly supplied with fenestrated capillaries, senses the ph, carbon dioxide, and oxygen concentrations in the blood and plays a crucial role in their homeostatic control.Carotid Arterial System: Anatomy
Glomus jugulare/tympanicum
Vagal
Laryngeal paraganglia of the head and neckNeckThe part of a human or animal body connecting the head to the rest of the body.Peritonsillar Abscess
Epidemiology[1,4,6]
Most common tumorTumorInflammation of adrenal medullaAdrenal MedullaThe inner portion of the adrenal gland. Derived from ectoderm, adrenal medulla consists mainly of chromaffin cells that produces and stores a number of neurotransmitters, mainly adrenaline (epinephrine) and norepinephrine. The activity of the adrenal medulla is regulated by the sympathetic nervous system.Adrenal Glands: Anatomy in adults
Approximately 1,000 cases diagnosed annually in the United States
Estimated 0.8 per 100,000 persons/year in the United States
Approximately 40% associated with hereditary disorders and younger age of onset
Etiology[4,6,8]
Chromaffin cell neoplasiaChromaffin Cell NeoplasiaPheochromocytoma (derived from the neural crestNeural crestThe two longitudinal ridges along the primitive streak appearing near the end of gastrulation during development of nervous system (neurulation). The ridges are formed by folding of neural plate. Between the ridges is a neural groove which deepens as the fold become elevated. When the folds meet at midline, the groove becomes a closed tube, the neural tube.Hirschsprung Disease)
25–40% of PPGL carry a germline (hereditary) mutationMutationGenetic mutations are errors in DNA that can cause protein misfolding and dysfunction. There are various types of mutations, including chromosomal, point, frameshift, and expansion mutations. Types of Mutations.
20+ geneGeneA category of nucleic acid sequences that function as units of heredity and which code for the basic instructions for the development, reproduction, and maintenance of organisms.Basic Terms of Genetics mutations have been identified in association with pheochromocytomaPheochromocytomaPheochromocytoma is a catecholamine-secreting tumor derived from chromaffin cells. The majority of tumors originate in the adrenal medulla, but they may also arise from sympathetic ganglia (also referred to as paraganglioma). Symptoms are associated with excessive catecholamine production and commonly include hypertension, tachycardia, headache, and sweating. Pheochromocytoma.
Most common genetic syndromes associated with pheochromocytomaPheochromocytomaPheochromocytoma is a catecholamine-secreting tumor derived from chromaffin cells. The majority of tumors originate in the adrenal medulla, but they may also arise from sympathetic ganglia (also referred to as paraganglioma). Symptoms are associated with excessive catecholamine production and commonly include hypertension, tachycardia, headache, and sweating. Pheochromocytoma:
Hereditary paraganglioma-pheochromcytoma syndrome (succinate dehydrogenaseSuccinate dehydrogenaseA flavoprotein containing oxidoreductase that catalyzes the dehydrogenation of succinate to fumarate. In most eukaryotic organisms this enzyme is a component of mitochondrial electron transport complex II.Citric Acid Cycle [SDHx ]mutations): single most common genetic cause of PPGL overall
Von Hippel-Lindau (VHL)
Multiple endocrine neoplasiaMultiple endocrine neoplasiaMultiple endocrine neoplasia syndromes are autosomal dominant inherited conditions characterized by 2 or more hormone-producing tumors involving the endocrine organs. There are different types of MEN, namely MEN1-4. Multiple Endocrine Neoplasia type 2 (MEN2)
Most pheochromocytomaPheochromocytomaPheochromocytoma is a catecholamine-secreting tumor derived from chromaffin cells. The majority of tumors originate in the adrenal medulla, but they may also arise from sympathetic ganglia (also referred to as paraganglioma). Symptoms are associated with excessive catecholamine production and commonly include hypertension, tachycardia, headache, and sweating. Pheochromocytoma secrete predominantly norepinephrineNorepinephrinePrecursor of epinephrine that is secreted by the adrenal medulla and is a widespread central and autonomic neurotransmitter. Norepinephrine is the principal transmitter of most postganglionic sympathetic fibers, and of the diffuse projection system in the brain that arises from the locus ceruleus.Receptors and Neurotransmitters of the CNS (normal medulla approximately 85% epinephrineEpinephrineThe active sympathomimetic hormone from the adrenal medulla. It stimulates both the alpha- and beta- adrenergic systems, causes systemic vasoconstriction and gastrointestinal relaxation, stimulates the heart, and dilates bronchi and cerebral vessels.Sympathomimetic Drugs); may also secret dopamineDopamineOne of the catecholamine neurotransmitters in the brain. It is derived from tyrosine and is the precursor to norepinephrine and epinephrine. Dopamine is a major transmitter in the extrapyramidal system of the brain, and important in regulating movement.Receptors and Neurotransmitters of the CNS.
Adrenal (intra-adrenal) pheochromocytomas:often have an adrenergic (epinephrineEpinephrineThe active sympathomimetic hormone from the adrenal medulla. It stimulates both the alpha- and beta- adrenergic systems, causes systemic vasoconstriction and gastrointestinal relaxation, stimulates the heart, and dilates bronchi and cerebral vessels.Sympathomimetic Drugs/metanephrineMetanephrineProduct of epinephrine o-methylation. It is a commonly occurring, pharmacologically and physiologically inactive metabolite of epinephrine.Pheochromocytoma) phenotypePhenotypeThe complete genetic complement contained in the DNA of a set of chromosomes in a human. The length of the human genome is about 3 billion base pairs.Basic Terms of Genetics with paroxysmal symptoms
Extra-adrenal and cluster-1 (SDHx/VHL) tumors: typically noradrenergic with more sustained hypertensionHypertensionHypertension, or high blood pressure, is a common disease that manifests as elevated systemic arterial pressures. Hypertension is most often asymptomatic and is found incidentally as part of a routine physical examination or during triage for an unrelated medical encounter. Hypertension
Predominantly dopamineDopamineOne of the catecholamine neurotransmitters in the brain. It is derived from tyrosine and is the precursor to norepinephrine and epinephrine. Dopamine is a major transmitter in the extrapyramidal system of the brain, and important in regulating movement.Receptors and Neurotransmitters of the CNS: very rare
SecretionSecretionCoagulation Studies is not regulated by neural pathways like the normal medulla (so release is autonomous).
Medications: inhibitors of catecholamine reuptake (e.g., tricyclic antidepressantsTricyclic antidepressantsTricyclic antidepressants (TCAs) are a class of medications used in the management of mood disorders, primarily depression. These agents, named after their 3-ring chemical structure, act via reuptake inhibition of neurotransmitters (particularly norepinephrine and serotonin) in the brain.Tricyclic Antidepressants)
GlucocorticoidsGlucocorticoidsGlucocorticoids are a class within the corticosteroid family. Glucocorticoids are chemically and functionally similar to endogenous cortisol. There are a wide array of indications, which primarily benefit from the antiinflammatory and immunosuppressive effects of this class of drugs.Glucocorticoids
Dopamine-D2 antagonists (metoclopramideMetoclopramideA dopamine d2 antagonist that is used as an antiemetic.Antiemetics)
Unopposed β-blockade
AnesthesiaAnesthesiaA state characterized by loss of feeling or sensation. This depression of nerve function is usually the result of pharmacologic action and is induced to allow performance of surgery or other painful procedures.Anesthesiology: History and Basic Concepts induction
↑ GlycogenolysisGlycogenolysisThe release of glucose from glycogen by glycogen phosphorylase (phosphorolysis). The released glucose-1-phosphate is then converted to glucose-6-phosphate by phosphoglucomutase before entering glycolysis. Glycogenolysis is stimulated by glucagon or epinephrine via the activation of phosphorylase kinase.Glycogen Metabolism
↑ GluconeogenesisGluconeogenesisGluconeogenesis is the process of making glucose from noncarbohydrate precursors. This metabolic pathway is more than just a reversal of glycolysis. Gluconeogenesis provides the body with glucose not obtained from food, such as during a fasting period. The production of glucose is critical for organs and cells that cannot use fat for fuel. Gluconeogenesis
↑ Intestinal relaxation
𝜷-adrenergic stimulation:
↑ Heart rateHeart rateThe number of times the heart ventricles contract per unit of time, usually per minute.Cardiac Physiology
Distant metastasisMetastasisThe transfer of a neoplasm from one organ or part of the body to another remote from the primary site.Grading, Staging, and Metastasis (may occur as late as 50 years after resection) to areas where chromaffin tissue is not normally found (boneBoneBone is a compact type of hardened connective tissue composed of bone cells, membranes, an extracellular mineralized matrix, and central bone marrow. The 2 primary types of bone are compact and spongy. Bones: Structure and Types, lung, liverLiverThe liver is the largest gland in the human body. The liver is found in the superior right quadrant of the abdomen and weighs approximately 1.5 kilograms. Its main functions are detoxification, metabolism, nutrient storage (e.g., iron and vitamins), synthesis of coagulation factors, formation of bile, filtration, and storage of blood. Liver: Anatomy, lymph nodesLymph NodesThey are oval or bean shaped bodies (1 – 30 mm in diameter) located along the lymphatic system.Lymphatic Drainage System: Anatomy)
All PCC/PGL:
Considered to have metastatic potential
There is no reliable histologic or biochemical feature that distinguishes indolent from metastatic tumors.
Clinical Presentation
Symptoms and signs of pheochromocytomaPheochromocytomaPheochromocytoma is a catecholamine-secreting tumor derived from chromaffin cells. The majority of tumors originate in the adrenal medulla, but they may also arise from sympathetic ganglia (also referred to as paraganglioma). Symptoms are associated with excessive catecholamine production and commonly include hypertension, tachycardia, headache, and sweating. Pheochromocytoma are typically paroxysmal.[1,4,6,8,10,13]
Classic triad (most patients rarely present with all 3 symptoms):
HeadacheHeadacheThe symptom of pain in the cranial region. It may be an isolated benign occurrence or manifestation of a wide variety of headache disorders.Brain Abscess: 90% of symptomatic patientsPatientsIndividuals participating in the health care system for the purpose of receiving therapeutic, diagnostic, or preventive procedures.Clinician–Patient Relationship
Sweating: 60%–70% of symptomatic patientsPatientsIndividuals participating in the health care system for the purpose of receiving therapeutic, diagnostic, or preventive procedures.Clinician–Patient Relationship
Hyperadrenergic spellsHyperadrenergic SpellsPheochromocytoma (pallor, anxietyAnxietyFeelings or emotions of dread, apprehension, and impending disaster but not disabling as with anxiety disorders.Generalized Anxiety Disorder, palpitationsPalpitationsEbstein’s Anomaly, tremorTremorCyclical movement of a body part that can represent either a physiologic process or a manifestation of disease. Intention or action tremor, a common manifestation of cerebellar diseases, is aggravated by movement. In contrast, resting tremor is maximal when there is no attempt at voluntary movement, and occurs as a relatively frequent manifestation of parkinson disease.Myotonic Dystrophies)
Orthostatic hypotensionOrthostatic hypotensionA significant drop in blood pressure after assuming a standing position. Orthostatic hypotension is a finding, and defined as a 20-mm hg decrease in systolic pressure or a 10-mm hg decrease in diastolic pressure 3 minutes after the person has risen from supine to standing. Symptoms generally include dizziness, blurred vision, and syncope.Hypotension (from catecholamine-induced volume contraction)
CardiomyopathyCardiomyopathyCardiomyopathy refers to a group of myocardial diseases associated with structural changes of the heart muscles (myocardium) and impaired systolic and/or diastolic function in the absence of other heart disorders (coronary artery disease, hypertension, valvular disease, and congenital heart disease). Cardiomyopathy: Overview and Types (catecholamine-induced)
5%–15% of patientsPatientsIndividuals participating in the health care system for the purpose of receiving therapeutic, diagnostic, or preventive procedures.Clinician–Patient Relationship may have normal blood pressure and no other symptoms:
Hyper- or hypotensionHypotensionHypotension is defined as low blood pressure, specifically < 90/60 mm Hg, and is most commonly a physiologic response. Hypotension may be mild, serious, or life threatening, depending on the cause. Hypotension
Hyperthermia (> 40℃)
Mental status changes
Multiple organ dysfunction
Mnemonic
To recall the most common clinical features of pheochromocytoma or episodic hyperadrenergic spells, remember the “5 Ps“:
Pressure (high blood pressure)
Pain (headacheHeadacheThe symptom of pain in the cranial region. It may be an isolated benign occurrence or manifestation of a wide variety of headache disorders.Brain Abscess)
Perspiration
Palpitations
Pallor
Diagnosis
Biochemical confirmation of the diagnosis should be followed by radiologic imaging to locate the tumorTumorInflammation.
History[4–6]
Presence of classic triad
Hyperadrenergic spellsHyperadrenergic SpellsPheochromocytoma (pallor, anxietyAnxietyFeelings or emotions of dread, apprehension, and impending disaster but not disabling as with anxiety disorders.Generalized Anxiety Disorder, palpitationsPalpitationsEbstein’s Anomaly, tremorTremorCyclical movement of a body part that can represent either a physiologic process or a manifestation of disease. Intention or action tremor, a common manifestation of cerebellar diseases, is aggravated by movement. In contrast, resting tremor is maximal when there is no attempt at voluntary movement, and occurs as a relatively frequent manifestation of parkinson disease.Myotonic Dystrophies)
HypertensionHypertensionHypertension, or high blood pressure, is a common disease that manifests as elevated systemic arterial pressures. Hypertension is most often asymptomatic and is found incidentally as part of a routine physical examination or during triage for an unrelated medical encounter. Hypertension onset at young age (< 20 years old)
HypertensionHypertensionHypertension, or high blood pressure, is a common disease that manifests as elevated systemic arterial pressures. Hypertension is most often asymptomatic and is found incidentally as part of a routine physical examination or during triage for an unrelated medical encounter. Hypertension with poor response to medications
Family historyFamily HistoryAdult Health Maintenance of pheochromocytomaPheochromocytomaPheochromocytoma is a catecholamine-secreting tumor derived from chromaffin cells. The majority of tumors originate in the adrenal medulla, but they may also arise from sympathetic ganglia (also referred to as paraganglioma). Symptoms are associated with excessive catecholamine production and commonly include hypertension, tachycardia, headache, and sweating. Pheochromocytoma
IdiopathicIdiopathicDermatomyositisdilated cardiomyopathyDilated CardiomyopathyDilated cardiomyopathy (DCM) is the most common type of non-ischemic cardiomyopathy and a common cause of heart failure (HF). The cause may be idiopathic, familial, or secondary to a variety of underlying conditions. The disease is characterized by the enlargement of 1 or both ventricles and reduced systolic function. Dilated Cardiomyopathy
Carney triadCarney TriadPheochromocytoma: gastric stromal tumors + pulmonary chondromas + paragangliomaParagangliomaA neural crest tumor usually derived from the chromoreceptor tissue of a paraganglion, such as the carotid body, or medulla of the adrenal gland (usually called a chromaffinoma or pheochromocytoma). It is more common in women than in men.Hearing Loss
Physical exam[6,10]
HypertensionHypertensionHypertension, or high blood pressure, is a common disease that manifests as elevated systemic arterial pressures. Hypertension is most often asymptomatic and is found incidentally as part of a routine physical examination or during triage for an unrelated medical encounter. Hypertension
TachycardiaTachycardiaAbnormally rapid heartbeat, usually with a heart rate above 100 beats per minute for adults. Tachycardia accompanied by disturbance in the cardiac depolarization (cardiac arrhythmia) is called tachyarrhythmia.Sepsis in Children
Pallor
Orthostatic hypotensionOrthostatic hypotensionA significant drop in blood pressure after assuming a standing position. Orthostatic hypotension is a finding, and defined as a 20-mm hg decrease in systolic pressure or a 10-mm hg decrease in diastolic pressure 3 minutes after the person has risen from supine to standing. Symptoms generally include dizziness, blurred vision, and syncope.Hypotension
Biochemical testing[4–6,8,12]
CatecholaminesCatecholaminesA general class of ortho-dihydroxyphenylalkylamines derived from tyrosine.Adrenal Hormones are metabolized to metanephrines in chromaffin cellsChromaffin cellsCells that store epinephrine secretory vesicles. During times of stress, the nervous system signals the vesicles to secrete their hormonal content. Their name derives from their ability to stain a brownish color with chromic salts. Characteristically, they are located in the adrenal medulla and paraganglia of the sympathetic nervous system.Adrenal Hormones, which can be measured in the urine and plasmaPlasmaThe residual portion of blood that is left after removal of blood cells by centrifugation without prior blood coagulation.Transfusion Products
PlasmaPlasmaThe residual portion of blood that is left after removal of blood cells by centrifugation without prior blood coagulation.Transfusion Products free fractionated metanephrines:
High sensitivity (96%–100%)
Poor specificity (85%–89%, in general; < 80% for patientsPatientsIndividuals participating in the health care system for the purpose of receiving therapeutic, diagnostic, or preventive procedures.Clinician–Patient Relationship > 60 years old)
Usually preferred test in children for whom 24-hour urine collection may be difficult
Draw sample when the patient is in the supine position.
24-hour urine for fractionated metanephrineMetanephrineProduct of epinephrine o-methylation. It is a commonly occurring, pharmacologically and physiologically inactive metabolite of epinephrine.Pheochromocytoma, vanillylmandelic acidVanillylmandelic AcidNeuroblastoma, and catecholaminesCatecholaminesA general class of ortho-dihydroxyphenylalkylamines derived from tyrosine.Adrenal Hormones:
Similar/lower sensitivity (77%–90%)
Better specificity than plasmaPlasmaThe residual portion of blood that is left after removal of blood cells by centrifugation without prior blood coagulation.Transfusion Products metanephrines (82%–98%)
Preferred 1st test in low-suspicion cases
Increases of ≥ 2–3 times the upper limitLimitA value (e.g., pressure or time) that should not be exceeded and which is specified by the operator to protect the lungInvasive Mechanical Ventilation of normal are expected for symptomatic pheochromocytomaPheochromocytomaPheochromocytoma is a catecholamine-secreting tumor derived from chromaffin cells. The majority of tumors originate in the adrenal medulla, but they may also arise from sympathetic ganglia (also referred to as paraganglioma). Symptoms are associated with excessive catecholamine production and commonly include hypertension, tachycardia, headache, and sweating. Pheochromocytoma.[4]
For patientsPatientsIndividuals participating in the health care system for the purpose of receiving therapeutic, diagnostic, or preventive procedures.Clinician–Patient Relationship with spells, testing should ideally be performed at the time of the spell.
Medications affecting test results:
Tricyclic antidepressantsTricyclic antidepressantsTricyclic antidepressants (TCAs) are a class of medications used in the management of mood disorders, primarily depression. These agents, named after their 3-ring chemical structure, act via reuptake inhibition of neurotransmitters (particularly norepinephrine and serotonin) in the brain.Tricyclic Antidepressants
Psychoactive medications
PhenoxybenzaminePhenoxybenzamineAn alpha-adrenergic antagonist with long duration of action. It has been used to treat hypertension and as a peripheral vasodilator.Antiadrenergic Drugs
Beta-blockersBeta-blockersDrugs that bind to but do not activate beta-adrenergic receptors thereby blocking the actions of beta-adrenergic agonists. Adrenergic beta-antagonists are used for treatment of hypertension, cardiac arrhythmias, angina pectoris, glaucoma, migraine headaches, and anxiety.Class 2 Antiarrhythmic Drugs (Beta Blockers)
LevodopaLevodopaThe naturally occurring form of dihydroxyphenylalanine and the immediate precursor of dopamine. Unlike dopamine itself, it can be taken orally and crosses the blood-brain barrier. It is rapidly taken up by dopaminergic neurons and converted to dopamine. It is used for the treatment of parkinsonian disorders and is usually given with agents that inhibit its conversion to dopamine outside of the central nervous system.Parkinson Disease Drugs
Imaging[4–6,8,9]
Once biochemical evidence of pheochromocytomaPheochromocytomaPheochromocytoma is a catecholamine-secreting tumor derived from chromaffin cells. The majority of tumors originate in the adrenal medulla, but they may also arise from sympathetic ganglia (also referred to as paraganglioma). Symptoms are associated with excessive catecholamine production and commonly include hypertension, tachycardia, headache, and sweating. Pheochromocytoma is obtained, imaging is performed:
a. For anatomical localization (CT or MRI), AND
b. For functional evaluation, identifying additional primary tumors, metastases, and targets for radionuclide therapy.
Anatomical imaging
Contrast-enhanced CT:
Usually 1st-line option
Excellent spatial resolution for thorax, abdomen, and pelvisPelvisThe pelvis consists of the bony pelvic girdle, the muscular and ligamentous pelvic floor, and the pelvic cavity, which contains viscera, vessels, and multiple nerves and muscles. The pelvic girdle, composed of 2 “hip” bones and the sacrum, is a ring-like bony structure of the axial skeleton that links the vertebral column with the lower extremities.Pelvis: Anatomy
MRI:
Alternative test
Recommended to evaluate metastatic PPGL and also to detect skullSkullThe skull (cranium) is the skeletal structure of the head supporting the face and forming a protective cavity for the brain. The skull consists of 22 bones divided into the viscerocranium (facial skeleton) and the neurocranium.Skull: Anatomy base and neckNeckThe part of a human or animal body connecting the head to the rest of the body.Peritonsillar Abscess paragangliomas
For patientsPatientsIndividuals participating in the health care system for the purpose of receiving therapeutic, diagnostic, or preventive procedures.Clinician–Patient Relationship with surgical clips (cause CT artifacts); check if clips are MRMRCalculated as the ratio of the total number of people who die due to all causes over a specific time period to the total number of people in the selected population.Measures of Health Status safe
For patientsPatientsIndividuals participating in the health care system for the purpose of receiving therapeutic, diagnostic, or preventive procedures.Clinician–Patient Relationship with an allergyAllergyAn abnormal adaptive immune response that may or may not involve antigen-specific IgEType I Hypersensitivity Reaction to CT contrast
Preferred in children, pregnant women, and those with recent excessive radiationRadiationEmission or propagation of acoustic waves (sound), electromagnetic energy waves (such as light; radio waves; gamma rays; or x-rays), or a stream of subatomic particles (such as electrons; neutrons; protons; or alpha particles).Osteosarcoma exposure
Both CT and MRI have high sensitivity in detecting sporadicSporadicSelective IgA Deficiency PCC, with choice depending on factors such as cost, radiationRadiationEmission or propagation of acoustic waves (sound), electromagnetic energy waves (such as light; radio waves; gamma rays; or x-rays), or a stream of subatomic particles (such as electrons; neutrons; protons; or alpha particles).Osteosarcoma exposure and use of IV contrast among others.
Preferred functional modality (especially for metastatic disease, SDHx-related tumors, and head-and-neck PGL)
Also able to assess receptorReceptorReceptors are proteins located either on the surface of or within a cell that can bind to signaling molecules known as ligands (e.g., hormones) and cause some type of response within the cell.Receptors expression relevant to peptide receptorReceptorReceptors are proteins located either on the surface of or within a cell that can bind to signaling molecules known as ligands (e.g., hormones) and cause some type of response within the cell.Receptors radionuclide therapy
[18F]-Fluoro-dihydroxyphenylalanine (F-DOPA) PETPETAn imaging technique that combines a positron-emission tomography (PET) scanner and a ct X ray scanner. This establishes a precise anatomic localization in the same session.Nuclear Imaging/CT:[16,17]
Most sensitive tracer for localizing sporadicSporadicSelective IgA Deficiency/primary pheochromocytomaPheochromocytomaPheochromocytoma is a catecholamine-secreting tumor derived from chromaffin cells. The majority of tumors originate in the adrenal medulla, but they may also arise from sympathetic ganglia (also referred to as paraganglioma). Symptoms are associated with excessive catecholamine production and commonly include hypertension, tachycardia, headache, and sweating. Pheochromocytoma
Performs well in detecting boneBoneBone is a compact type of hardened connective tissue composed of bone cells, membranes, an extracellular mineralized matrix, and central bone marrow. The 2 primary types of bone are compact and spongy. Bones: Structure and TypesmetastasisMetastasisThe transfer of a neoplasm from one organ or part of the body to another remote from the primary site.Grading, Staging, and Metastasis (but ⁶⁸Ga-DOTATATE remains the preferred tracer for skeletal/metastatic disease)
Not FDA-approved for PPGL application in the US (used in Europe)
18F-fluorodeoxyglucose (FDG) PETPETAn imaging technique that combines a positron-emission tomography (PET) scanner and a ct X ray scanner. This establishes a precise anatomic localization in the same session.Nuclear Imaging/CT:
Note: PETPETAn imaging technique that combines a positron-emission tomography (PET) scanner and a ct X ray scanner. This establishes a precise anatomic localization in the same session.Nuclear Imaging imaging is contraindicated in pregnant women.
IodineIodineA nonmetallic element of the halogen group that is represented by the atomic symbol I, atomic number 53, and atomic weight of 126. 90. It is a nutritionally essential element, especially important in thyroid hormone synthesis. In solution, it has anti-infective properties and is used topically.Thyroid Hormones metaiodobenzylguanidine (MIBGMIBGPheochromocytoma) scintigraphyScintigraphySjögren Syndrome:
Radioactive iodineRadioactive iodineUnstable isotopes of iodine that decay or disintegrate emitting radiation. I atoms with atomic weights 117-139, except I 127, are radioactive iodine isotopes.Antithyroid Drugs (iobenguane-123) taken by adrenergic tissues similar to norepinephrineNorepinephrinePrecursor of epinephrine that is secreted by the adrenal medulla and is a widespread central and autonomic neurotransmitter. Norepinephrine is the principal transmitter of most postganglionic sympathetic fibers, and of the diffuse projection system in the brain that arises from the locus ceruleus.Receptors and Neurotransmitters of the CNS
Less sensitive than FDG-PET and DOTATATE
Can detect multiple tumors or tumors not visualized on CT or MRI
Utilized for confirmation of tumorTumorInflammation avidity before ¹³¹I-MIBG (iobenguane) radionuclide therapy
IMPORTANT NOTE: image-guided biopsyBiopsyRemoval and pathologic examination of specimens from the living body.Ewing Sarcoma → may precipitate catecholamine release and severe hypertensive crisisHypertensive CrisisOxazolidinones
Exclude a catecholamine-secreting tumorTumorInflammation biochemically (plasmaPlasmaThe residual portion of blood that is left after removal of blood cells by centrifugation without prior blood coagulation.Transfusion Products free or urinary fractionated metanephrines) before biopsying any adrenal or indeterminate retroperitonealRetroperitonealPeritoneum: AnatomymassMassThree-dimensional lesion that occupies a space within the breastImaging of the Breast.
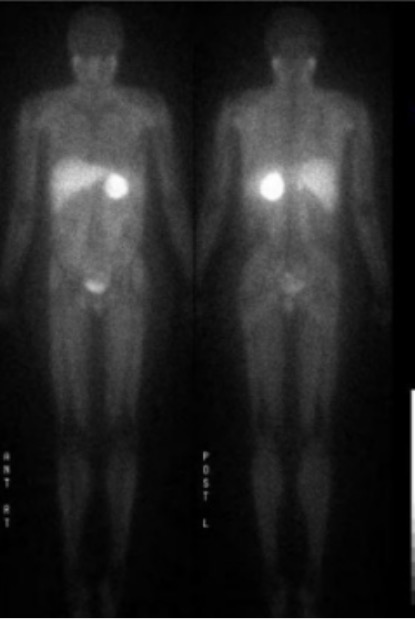
Intense uptake by an adrenal mass (pheochromocytoma) as shown on a 123I-MIBG scan
Image: “123I-MIBG scan” by Endocrine Unit, Department of Medicine, University of Rochester, Rochester, NY, 14642, USA. License: CC BY 2.0, cropped by Lecturio.
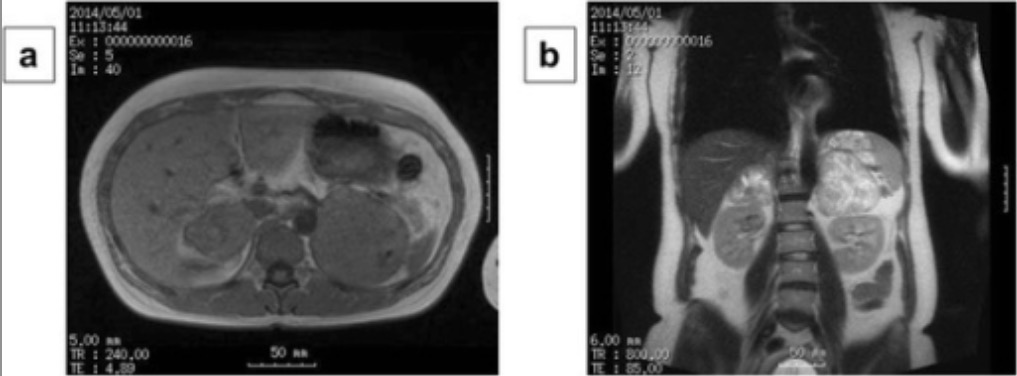
Bilateral adrenal pheochromocytoma with central necrosis as shown on MRI
Image: “MRI findings” by Department of Surgical Oncology, Osaka City University Graduate School of Medicine, 1-4-3 Asahi-machi, Abeno-ku, Osaka, Japan. License: CC BY 4.0
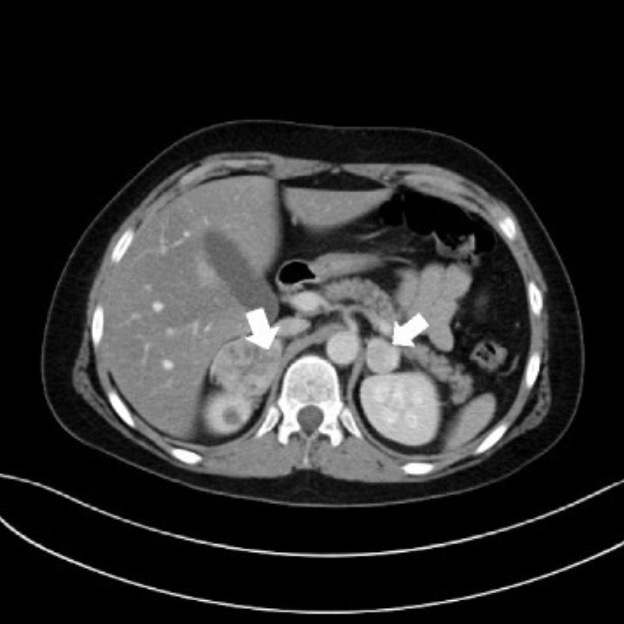
Bilateral adrenal pheochromocytoma in a patient with VHL disease
Image: “Bilateral nodular lesions” by Department of Paediatric Endocrinology and Diabetology, Medical University in Lublin, Poland, ul. Prof. A. Gebali 6, 20-093, Lublin, Poland. License: CC BY 4.0
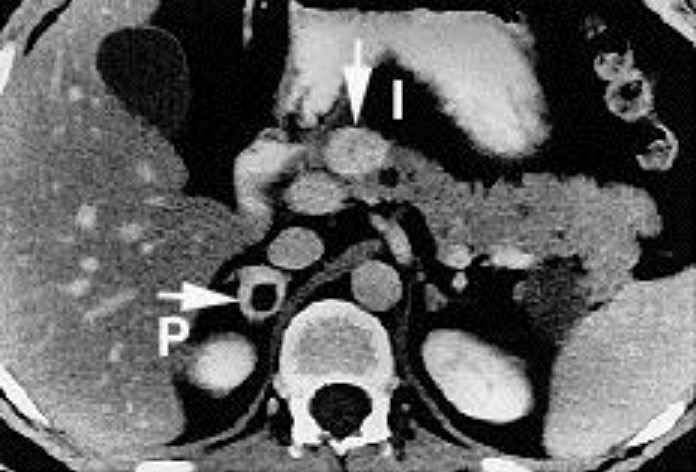
Computed tomography of a patient presenting simultaneous pheochromocytoma and islet cell tumor of the pancreas: Note the pheochromocytoma has necrotic center.
Image: “A symptomatic patient with pheochromocytoma” by United States Government. License: Public Domain
Genetic testingGenetic TestingDetection of a mutation; genotype; karyotype; or specific alleles associated with genetic traits, heritable diseases, or predisposition to a disease, or that may lead to the disease in descendants. It includes prenatal genetic testing.Myotonic Dystrophies[4–7,15]
Germline testing for allpatientsPatientsIndividuals participating in the health care system for the purpose of receiving therapeutic, diagnostic, or preventive procedures.Clinician–Patient Relationship with PPGL.
Refer the patient to a genetic counselor for a risk evaluation for a hereditary syndrome.
Personal or family historyFamily HistoryAdult Health Maintenance of clinical features suggestive of hereditary pheochromocytomaPheochromocytomaPheochromocytoma is a catecholamine-secreting tumor derived from chromaffin cells. The majority of tumors originate in the adrenal medulla, but they may also arise from sympathetic ganglia (also referred to as paraganglioma). Symptoms are associated with excessive catecholamine production and commonly include hypertension, tachycardia, headache, and sweating. Pheochromocytoma–paragangliomaParagangliomaA neural crest tumor usually derived from the chromoreceptor tissue of a paraganglion, such as the carotid body, or medulla of the adrenal gland (usually called a chromaffinoma or pheochromocytoma). It is more common in women than in men.Hearing Loss syndrome
Sympathetic or malignant extra-adrenal paragangliomas
Age < 40 years
If a mutationMutationGenetic mutations are errors in DNA that can cause protein misfolding and dysfunction. There are various types of mutations, including chromosomal, point, frameshift, and expansion mutations. Types of Mutations is identified, predictive genetic testingGenetic TestingDetection of a mutation; genotype; karyotype; or specific alleles associated with genetic traits, heritable diseases, or predisposition to a disease, or that may lead to the disease in descendants. It includes prenatal genetic testing.Myotonic Dystrophies should be offered to asymptomatic at-risk family members.
Management may vary depending on practice location. The following information is based on US, UK, and European literature and guidelines for adult patientsPatientsIndividuals participating in the health care system for the purpose of receiving therapeutic, diagnostic, or preventive procedures.Clinician–Patient Relationship. A multidisciplinary team, including endocrinology, oncology, and surgery, can help guide therapeutic decisions.
Once a pheochromocytomaPheochromocytomaPheochromocytoma is a catecholamine-secreting tumor derived from chromaffin cells. The majority of tumors originate in the adrenal medulla, but they may also arise from sympathetic ganglia (also referred to as paraganglioma). Symptoms are associated with excessive catecholamine production and commonly include hypertension, tachycardia, headache, and sweating. Pheochromocytoma is diagnosed, all patientsPatientsIndividuals participating in the health care system for the purpose of receiving therapeutic, diagnostic, or preventive procedures.Clinician–Patient Relationship should undergo resection (if possible), following appropriate medical preparation.[3,5]
Surgery[4–6,10,14]
Only definitive treatment
Minimally invasive (laparoscopic or robotic) adrenalectomyAdrenalectomyExcision of one or both adrenal glands.Cushing Syndrome is the standard of careStandard of careThe minimum acceptable patient care, based on statutes, court decisions, policies, or professional guidelines.Malpractice for adrenal pheochromocytomaPheochromocytomaPheochromocytoma is a catecholamine-secreting tumor derived from chromaffin cells. The majority of tumors originate in the adrenal medulla, but they may also arise from sympathetic ganglia (also referred to as paraganglioma). Symptoms are associated with excessive catecholamine production and commonly include hypertension, tachycardia, headache, and sweating. Pheochromocytoma.
Bilateral partial adrenalectomyAdrenalectomyExcision of one or both adrenal glands.Cushing Syndrome or cortical-sparing adrenalectomyAdrenalectomyExcision of one or both adrenal glands.Cushing Syndrome should be performed for bilateral lesions.
Cortical-sparing (not total bilateral) adrenalectomyAdrenalectomyExcision of one or both adrenal glands.Cushing Syndrome for MEN2, because MEN2 is a low-metastatic-risk syndrome and high risk for bilaterality.
Total adrenalectomyAdrenalectomyExcision of one or both adrenal glands.Cushing Syndrome is generally reserved for high-metastatic-risk genotypes such as SDHSDHSubdural hemorrhage (SDH) is bleeding into the space between the dural and arachnoid meningeal layers surrounding the brain. The most common mechanism triggering the bleeding event is trauma (e.g., closed head injury) causing a tearing injury to the extracerebral “bridging” veins.Subdural HemorrhagemutationMutationGenetic mutations are errors in DNA that can cause protein misfolding and dysfunction. There are various types of mutations, including chromosomal, point, frameshift, and expansion mutations. Types of Mutations
Laparoscopic resection also feasible for some abdominal paragangliomas
Open resections reserved for large, difficult-to-access, or locally invasive tumors
Preoperative preparation
Goals:[5,10,18]
Control hypertensionHypertensionHypertension, or high blood pressure, is a common disease that manifests as elevated systemic arterial pressures. Hypertension is most often asymptomatic and is found incidentally as part of a routine physical examination or during triage for an unrelated medical encounter. Hypertension and tachycardiaTachycardiaAbnormally rapid heartbeat, usually with a heart rate above 100 beats per minute for adults. Tachycardia accompanied by disturbance in the cardiac depolarization (cardiac arrhythmia) is called tachyarrhythmia.Sepsis in Children to prevent hypertensive crisisHypertensive CrisisOxazolidinones.
Blood pressure goals:
Seated blood pressure < 130/80 mm Hg
Standing systolic pressure > 90 mm Hg
Heart rateHeart rateThe number of times the heart ventricles contract per unit of time, usually per minute.Cardiac Physiology goals:
Seated: 60–70 beats/min
Standing: 70–90 beats/min
Volume expansion with IV fluidsIV fluidsIntravenous fluids are one of the most common interventions administered in medicine to approximate physiologic bodily fluids. Intravenous fluids are divided into 2 categories: crystalloid and colloid solutions. Intravenous fluids have a wide variety of indications, including intravascular volume expansion, electrolyte manipulation, and maintenance fluids. Intravenous Fluids
Medical therapy:[3–6,10,18]
α-Adrenergic blockade:
To control hypertensionHypertensionHypertension, or high blood pressure, is a common disease that manifests as elevated systemic arterial pressures. Hypertension is most often asymptomatic and is found incidentally as part of a routine physical examination or during triage for an unrelated medical encounter. Hypertension and prevent volume contraction
Started at least 7–14 days preoperatively and titrated to hit blood pressure target
Options:
α-blockade with either a selective α₁ agent (doxazosinDoxazosinA prazosin-related compound that is a selective alpha-1-adrenergic blocker.Antiadrenergic Drugs, terazosinTerazosinAntiadrenergic Drugs, prazosinPrazosinA selective adrenergic alpha-1 antagonist used in the treatment of heart failure; hypertension; pheochromocytoma; raynaud disease; prostatic hypertrophy; and urinary retention.Antiadrenergic Drugs) OR
Nonselective agent phenoxybenzaminePhenoxybenzamineAn alpha-adrenergic antagonist with long duration of action. It has been used to treat hypertension and as a peripheral vasodilator.Antiadrenergic Drugs
High-sodium and fluid diet:
Started on 2nd–3rd day of α-blockade
Aids in volume expansion
Reduces risk of orthostatic hypotensionOrthostatic hypotensionA significant drop in blood pressure after assuming a standing position. Orthostatic hypotension is a finding, and defined as a 20-mm hg decrease in systolic pressure or a 10-mm hg decrease in diastolic pressure 3 minutes after the person has risen from supine to standing. Symptoms generally include dizziness, blurred vision, and syncope.Hypotension due to medications
𝛃-Adrenergic blockade:
To control tachycardiaTachycardiaAbnormally rapid heartbeat, usually with a heart rate above 100 beats per minute for adults. Tachycardia accompanied by disturbance in the cardiac depolarization (cardiac arrhythmia) is called tachyarrhythmia.Sepsis in Children
Usually started 3–4 days after initiating α-adrenergic blockade and after volume expansion has been accomplished
CalciumCalciumA basic element found in nearly all tissues. It is a member of the alkaline earth family of metals with the atomic symbol ca, atomic number 20, and atomic weight 40. Calcium is the most abundant mineral in the body and combines with phosphorus to form calcium phosphate in the bones and teeth. It is essential for the normal functioning of nerves and muscles and plays a role in blood coagulation (as factor IV) and in many enzymatic processes.Electrolytes channel blockers:
May also be added for additional blood pressure control
Use as monotherapy (in place of α-adrenergic blockade) is rarely indicated.
Can add for a short period before surgery if α-blockade is not effective enough to control blood pressure.
Table: Preoperative medication dosing for pheochromocytomaPheochromocytomaPheochromocytoma is a catecholamine-secreting tumor derived from chromaffin cells. The majority of tumors originate in the adrenal medulla, but they may also arise from sympathetic ganglia (also referred to as paraganglioma). Symptoms are associated with excessive catecholamine production and commonly include hypertension, tachycardia, headache, and sweating. Pheochromocytoma[3,5]
Class
Medication options
Initial dosing
Alpha-adrenergic blocker
PhenoxybenzaminePhenoxybenzamineAn alpha-adrenergic antagonist with long duration of action. It has been used to treat hypertension and as a peripheral vasodilator.Antiadrenergic Drugs
MetoprololMetoprololA selective adrenergic beta-1 blocking agent that is commonly used to treat angina pectoris; hypertension; and cardiac arrhythmias.Antiadrenergic Drugs
CalciumCalciumA basic element found in nearly all tissues. It is a member of the alkaline earth family of metals with the atomic symbol ca, atomic number 20, and atomic weight 40. Calcium is the most abundant mineral in the body and combines with phosphorus to form calcium phosphate in the bones and teeth. It is essential for the normal functioning of nerves and muscles and plays a role in blood coagulation (as factor IV) and in many enzymatic processes.Electrolytes channel blocker
AmlodipineAmlodipineA long-acting dihydropyridine calcium channel blocker. It is effective in the treatment of angina pectoris and hypertension.Hypertension Drugs
RadiationRadiationEmission or propagation of acoustic waves (sound), electromagnetic energy waves (such as light; radio waves; gamma rays; or x-rays), or a stream of subatomic particles (such as electrons; neutrons; protons; or alpha particles).Osteosarcoma therapy
Percutaneous ethanolEthanolA clear, colorless liquid rapidly absorbed from the gastrointestinal tract and distributed throughout the body. It has bactericidal activity and is used often as a topical disinfectant. It is widely used as a solvent and preservative in pharmaceutical preparations as well as serving as the primary ingredient in alcoholic beverages.Ethanol Metabolism injection
Chemoembolization (for liverLiverThe liver is the largest gland in the human body. The liver is found in the superior right quadrant of the abdomen and weighs approximately 1.5 kilograms. Its main functions are detoxification, metabolism, nutrient storage (e.g., iron and vitamins), synthesis of coagulation factors, formation of bile, filtration, and storage of blood. Liver: AnatomymetastasisMetastasisThe transfer of a neoplasm from one organ or part of the body to another remote from the primary site.Grading, Staging, and Metastasis)
Palliative radiationRadiationEmission or propagation of acoustic waves (sound), electromagnetic energy waves (such as light; radio waves; gamma rays; or x-rays), or a stream of subatomic particles (such as electrons; neutrons; protons; or alpha particles).Osteosarcoma therapy
Specific treatments for unresectable disease:
CytotoxicCytotoxicParvovirus B19 therapy (cyclophosphamideCyclophosphamidePrecursor of an alkylating nitrogen mustard antineoplastic and immunosuppressive agent that must be activated in the liver to form the active aldophosphamide. It has been used in the treatment of lymphoma and leukemia. Its side effect, alopecia, has been used for defleecing sheep. Cyclophosphamide may also cause sterility, birth defects, mutations, and cancer.Immunosuppressants, dacarbazineDacarbazineAn antineoplastic agent. It has significant activity against melanomas.Alkylating Agents and Platinum, vincristineVincristineAn antitumor alkaloid isolated from vinca rosea.Microtubule and Topoisomerase Inhibitors, doxorubicin)
TyrosineTyrosineA non-essential amino acid. In animals it is synthesized from phenylalanine. It is also the precursor of epinephrine; thyroid hormones; and melanin.Synthesis of Nonessential Amino Acids kinase receptorReceptorReceptors are proteins located either on the surface of or within a cell that can bind to signaling molecules known as ligands (e.g., hormones) and cause some type of response within the cell.Receptors inhibitors:
Sunitinib or cabozantinib
Selpercatinib for RET-fusion tumors
Belzutifan:
Oral HIF-2α inhibitor
For locally advanced, unresectable, or metastatic PPGL in patientsPatientsIndividuals participating in the health care system for the purpose of receiving therapeutic, diagnostic, or preventive procedures.Clinician–Patient Relationship ≥12 years
SomatostatinSomatostatinA 14-amino acid peptide named for its ability to inhibit pituitary growth hormone release, also called somatotropin release-inhibiting factor. It is expressed in the central and peripheral nervous systems, the gut, and other organs. SRIF can also inhibit the release of thyroid-stimulating hormone; prolactin; insulin; and glucagon besides acting as a neurotransmitter and neuromodulator. In a number of species including humans, there is an additional form of somatostatin, srif-28 with a 14-amino acid extension at the n-terminal.Gastrointestinal Secretions analogs:
For slowly progressive somatostatinSomatostatinA 14-amino acid peptide named for its ability to inhibit pituitary growth hormone release, also called somatotropin release-inhibiting factor. It is expressed in the central and peripheral nervous systems, the gut, and other organs. SRIF can also inhibit the release of thyroid-stimulating hormone; prolactin; insulin; and glucagon besides acting as a neurotransmitter and neuromodulator. In a number of species including humans, there is an additional form of somatostatin, srif-28 with a 14-amino acid extension at the n-terminal.Gastrointestinal SecretionsreceptorReceptorReceptors are proteins located either on the surface of or within a cell that can bind to signaling molecules known as ligands (e.g., hormones) and cause some type of response within the cell.Receptors (SSTR)-positive PPGL
OctreotideOctreotideA potent, long-acting synthetic somatostatin octapeptide analog that inhibits secretion of growth hormone and is used to treat hormone-secreting tumors; diabetes mellitus; hypotension, orthostatic; hyperinsulinism; hypergastrinemia; and small bowel fistula.Antidiarrheal Drugs or lanreotide
Similar in structure to norepinephrineNorepinephrinePrecursor of epinephrine that is secreted by the adrenal medulla and is a widespread central and autonomic neurotransmitter. Norepinephrine is the principal transmitter of most postganglionic sympathetic fibers, and of the diffuse projection system in the brain that arises from the locus ceruleus.Receptors and Neurotransmitters of the CNS, thus taken up by sympathetic nerve cells, including those of the pheochromocytomaPheochromocytomaPheochromocytoma is a catecholamine-secreting tumor derived from chromaffin cells. The majority of tumors originate in the adrenal medulla, but they may also arise from sympathetic ganglia (also referred to as paraganglioma). Symptoms are associated with excessive catecholamine production and commonly include hypertension, tachycardia, headache, and sweating. Pheochromocytoma
¹³¹I-MIBG: effective but was commercially withdrawn
Peptide receptorReceptorReceptors are proteins located either on the surface of or within a cell that can bind to signaling molecules known as ligands (e.g., hormones) and cause some type of response within the cell.Receptors radionuclide therapy:
Lutetium Lu-177 dotatate for tumors that express SSTRs
Limited data
Those with poorly controlled hypertensionHypertensionHypertension, or high blood pressure, is a common disease that manifests as elevated systemic arterial pressures. Hypertension is most often asymptomatic and is found incidentally as part of a routine physical examination or during triage for an unrelated medical encounter. Hypertension pre-treatment are at high risk for catecholamine crisis.
Palliative therapy
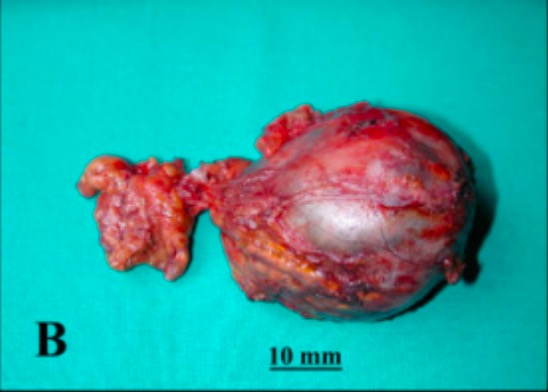
Pheochromocytoma of left adrenal gland (post-resection)
Image: “Pre-surgical MR and macroscopic anatomy images” by Non-invasive Cardiac Imaging Laboratory, CMR Unit, Department of Cardiology and Cardiovascular Surgery, Niguarda Ca’Granda Hospital, Milan, Italy. License: CC BY 2.0, cropped by Lecturio.
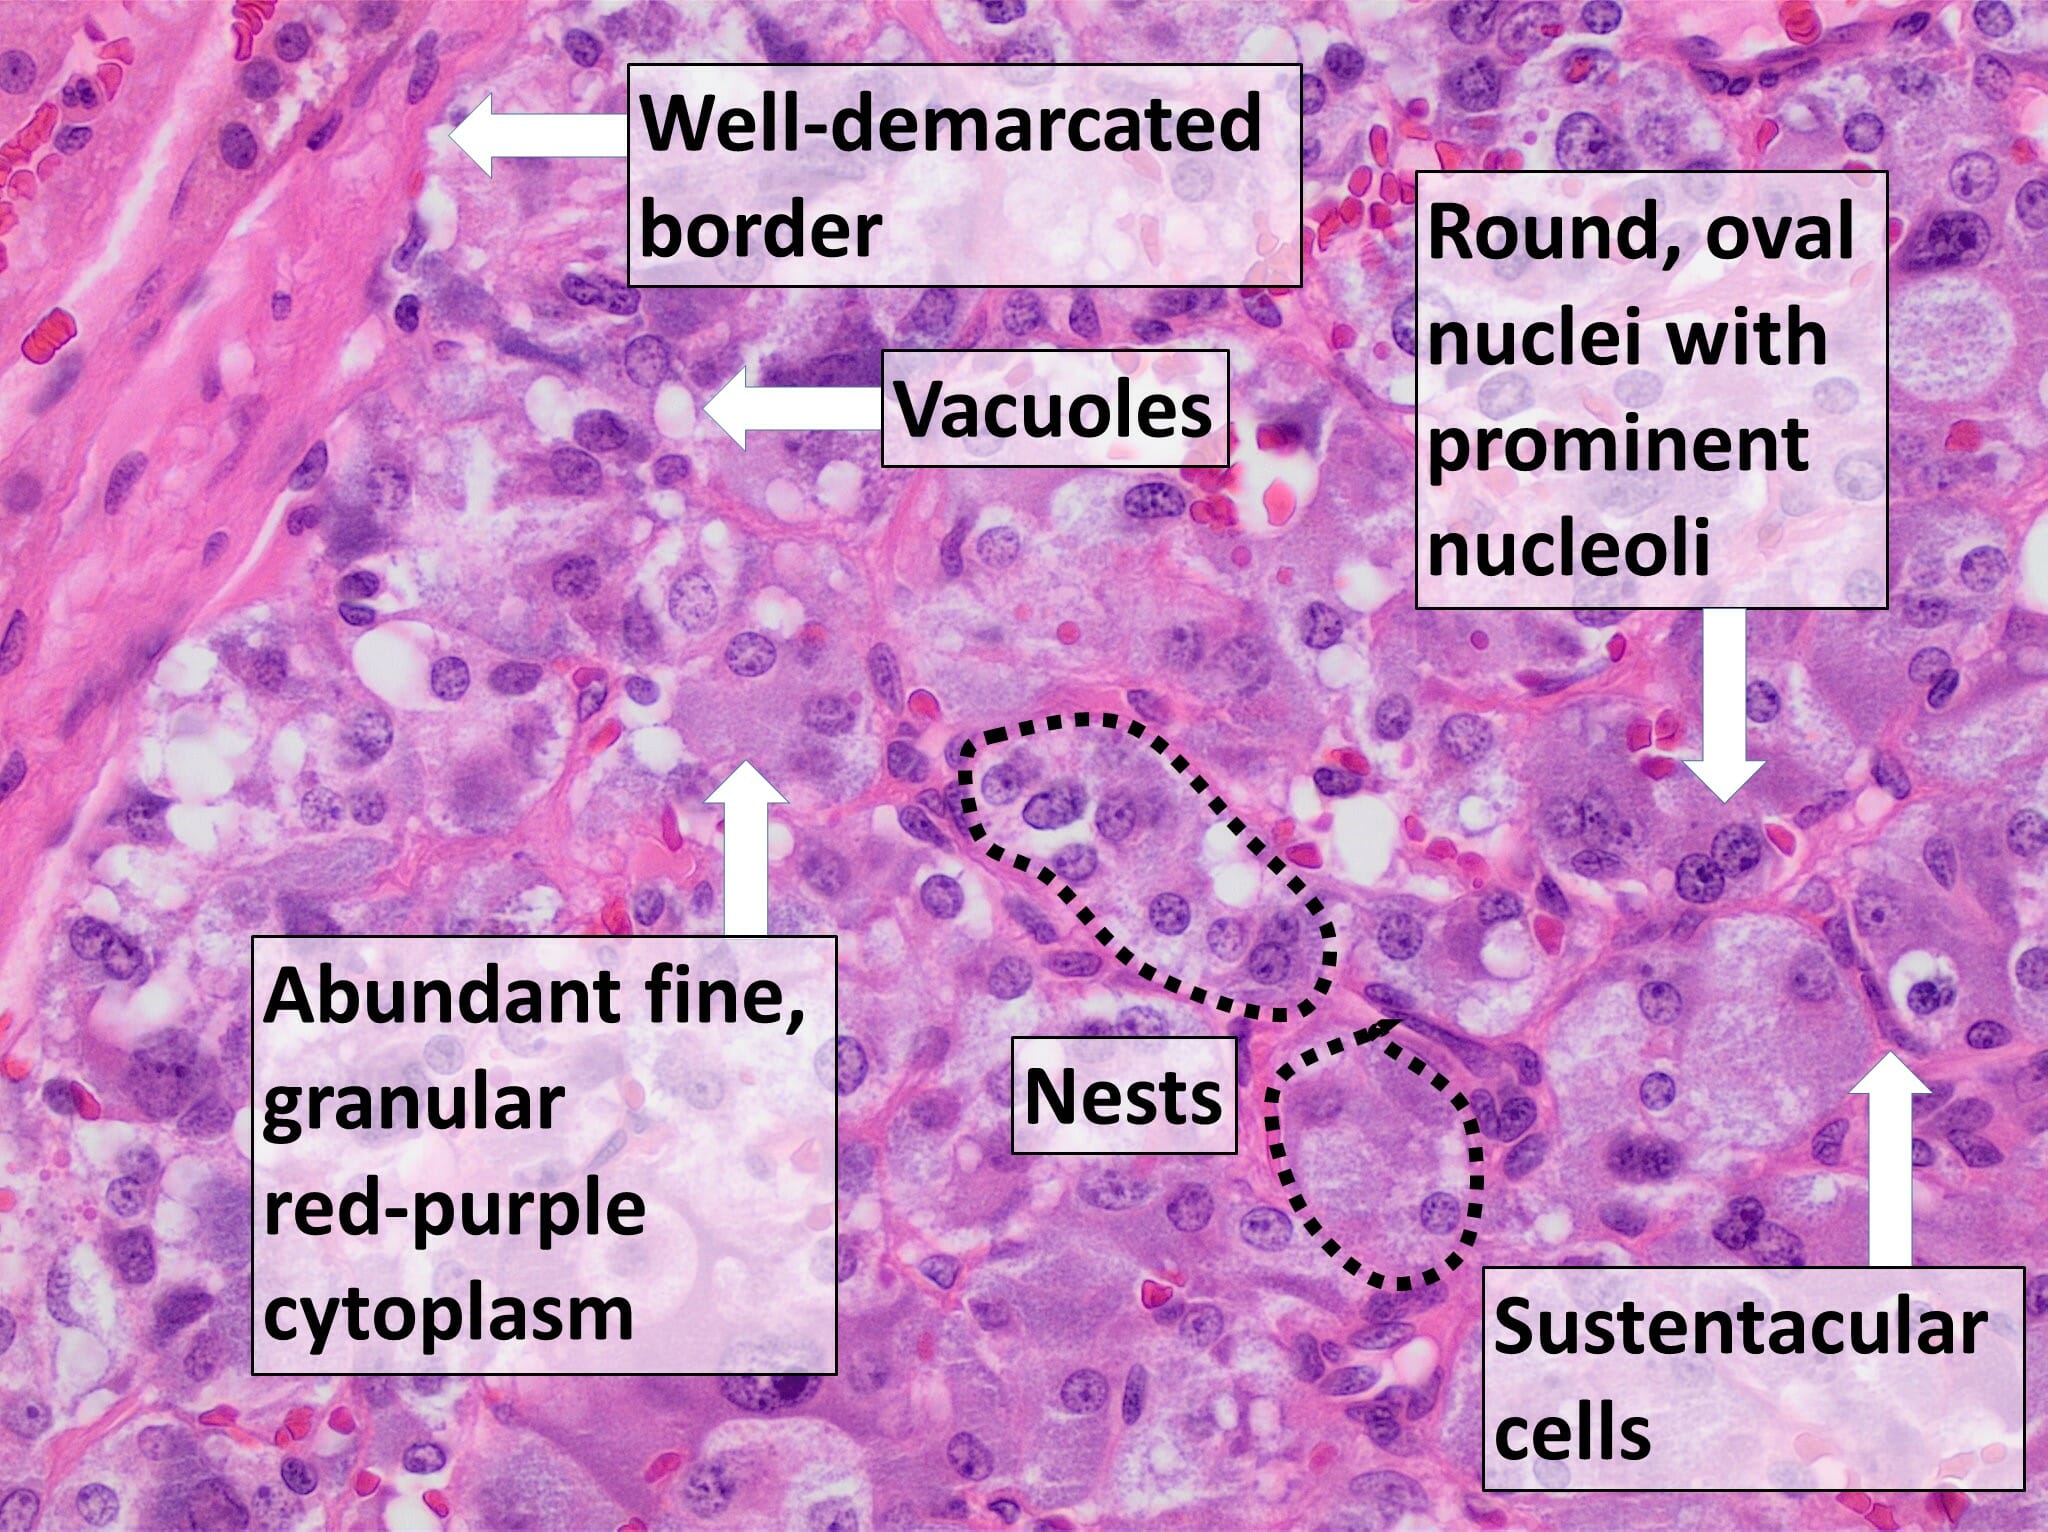
Histological specimen of pheochromocytoma:
The diagnosis of pheochromocytoma is confirmed by microscopic evaluation of the resected tumor after surgical resection. The important features observed include nests or trabecular arrangement of cells, extensive vacuolation of cells, large and polygonal sustentacular cells, granular red-purple cytoplasm, round or oval nuclei, and prominent nucleoli.
Image: “Histopathology of pheochromocytoma” by Mikael Häggström. License: Public Domain
HypertensionHypertensionHypertension, or high blood pressure, is a common disease that manifests as elevated systemic arterial pressures. Hypertension is most often asymptomatic and is found incidentally as part of a routine physical examination or during triage for an unrelated medical encounter. Hypertension or hypotensionHypotensionHypotension is defined as low blood pressure, specifically < 90/60 mm Hg, and is most commonly a physiologic response. Hypotension may be mild, serious, or life threatening, depending on the cause. Hypotension (hemodynamic instability)
Arrhythmias
Rebound hypoglycemiaHypoglycemiaHypoglycemia is an emergency condition defined as a serum glucose level ≤ 70 mg/dL (≤ 3.9 mmol/L) in diabetic patients. In nondiabetic patients, there is no specific or defined limit for normal serum glucose levels, and hypoglycemia is defined mainly by its clinical features. Hypoglycemia
Adrenal insufficiencyAdrenal InsufficiencyConditions in which the production of adrenal corticosteroids falls below the requirement of the body. Adrenal insufficiency can be caused by defects in the adrenal glands, the pituitary gland, or the hypothalamus.Adrenal Insufficiency and Addison Disease (if bilateral tumors removed)
Monitor closely for 24–48 hours:
Blood pressure
Heart rateHeart rateThe number of times the heart ventricles contract per unit of time, usually per minute.Cardiac Physiology
GlucoseGlucoseA primary source of energy for living organisms. It is naturally occurring and is found in fruits and other parts of plants in its free state. It is used therapeutically in fluid and nutrient replacement.Lactose Intolerance
Adjust medications as needed.
If adrenal insufficiencyAdrenal InsufficiencyConditions in which the production of adrenal corticosteroids falls below the requirement of the body. Adrenal insufficiency can be caused by defects in the adrenal glands, the pituitary gland, or the hypothalamus.Adrenal Insufficiency and Addison Disease is a potential complication → cosyntropin-stimulation test
Follow-up[4,5,8,10,12,15]
Owing to the risk of recurrence, patientsPatientsIndividuals participating in the health care system for the purpose of receiving therapeutic, diagnostic, or preventive procedures.Clinician–Patient Relationship should be educated on the importance of long-term follow-up.
Obtain testing postoperatively: metanephrines stay falsely elevated for ~10–14 days
European guidelines recommend repeat test 2–6 weeks after surgery[10]
12 weeks–12 months post-resection:
History and physical, blood pressure
PlasmaPlasmaThe residual portion of blood that is left after removal of blood cells by centrifugation without prior blood coagulation.Transfusion Products free or 24-h urine fractionated metanephrines/catecholaminesCatecholaminesA general class of ortho-dihydroxyphenylalkylamines derived from tyrosine.Adrenal Hormones
Consider chest CT (± contrast) and abdomen/pelvisPelvisThe pelvis consists of the bony pelvic girdle, the muscular and ligamentous pelvic floor, and the pelvic cavity, which contains viscera, vessels, and multiple nerves and muscles. The pelvic girdle, composed of 2 “hip” bones and the sacrum, is a ring-like bony structure of the axial skeleton that links the vertebral column with the lower extremities.Pelvis: Anatomy CT or MRI with contrast (If results of postsurgical biochemical testing are elevated → repeat imaging 3–6 months after surgery would be indicated)[10]
>12 months:
History and physical, blood pressure
Biochemical markers annually (or sooner if symptomatic), with imaging considered
Follow-up CT, MRI, or functional imaging may be ordered every 2–3 years, depending on tumorTumorInflammation characteristics and metastatic potential.
PrognosisPrognosisA prediction of the probable outcome of a disease based on a individual’s condition and the usual course of the disease as seen in similar situations.Non-Hodgkin Lymphomas[4]
For malignant/metastatic disease, prognosisPrognosisA prediction of the probable outcome of a disease based on a individual’s condition and the usual course of the disease as seen in similar situations.Non-Hodgkin Lymphomas depends on:
HyperthyroidismHyperthyroidismHypersecretion of thyroid hormones from the thyroid gland. Elevated levels of thyroid hormones increase basal metabolic rate.Thyrotoxicosis and Hyperthyroidism: a condition caused by excessive secretionSecretionCoagulation Studies of thyroidThyroidThe thyroid gland is one of the largest endocrine glands in the human body. The thyroid gland is a highly vascular, brownish-red gland located in the visceral compartment of the anterior region of the neck.Thyroid Gland: Anatomy hormone by the thyroidThyroidThe thyroid gland is one of the largest endocrine glands in the human body. The thyroid gland is a highly vascular, brownish-red gland located in the visceral compartment of the anterior region of the neck.Thyroid Gland: Anatomy gland. Presentation can include anxietyAnxietyFeelings or emotions of dread, apprehension, and impending disaster but not disabling as with anxiety disorders.Generalized Anxiety Disorder, sweating, palpitationsPalpitationsEbstein’s Anomaly, and heatHeatInflammation intolerance. The diagnosis is established by measurement of plasmaPlasmaThe residual portion of blood that is left after removal of blood cells by centrifugation without prior blood coagulation.Transfusion Products levels of thyroidThyroidThe thyroid gland is one of the largest endocrine glands in the human body. The thyroid gland is a highly vascular, brownish-red gland located in the visceral compartment of the anterior region of the neck.Thyroid Gland: Anatomy hormone (free T4T4The major hormone derived from the thyroid gland. Thyroxine is synthesized via the iodination of tyrosines (monoiodotyrosine) and the coupling of iodotyrosines (diiodotyrosine) in the thyroglobulin. Thyroxine is released from thyroglobulin by proteolysis and secreted into the blood. Thyroxine is peripherally deiodinated to form triiodothyronine which exerts a broad spectrum of stimulatory effects on cell metabolism.Thyroid Hormones) and thyroid-stimulating hormoneThyroid-stimulating hormoneA glycoprotein hormone secreted by the adenohypophysis. Thyrotropin stimulates thyroid gland by increasing the iodide transport, synthesis and release of thyroid hormones (thyroxine and triiodothyronine).Thyroid Hormones.
AnxietyAnxietyFeelings or emotions of dread, apprehension, and impending disaster but not disabling as with anxiety disorders.Generalized Anxiety Disorder disorder: psychiatric disorder often associated with physical manifestations. Presentation can include palpitationsPalpitationsEbstein’s Anomaly, sweating, tremors, and shortness of breathShortness of breathDyspnea is the subjective sensation of breathing discomfort. Dyspnea is a normal manifestation of heavy physical or psychological exertion, but also may be caused by underlying conditions (both pulmonary and extrapulmonary).Dyspnea. The diagnosis is established by ruling out other medical conditions.
Carcinoid syndromeCarcinoid syndromeA symptom complex associated with carcinoid tumor and characterized by attacks of severe flushing of the skin, diarrheal watery stools, bronchoconstriction, sudden drops in blood pressure, edema, and ascites. The carcinoid tumors are usually located in the gastrointestinal tract and metastasize to the liver. Symptoms are caused by tumor secretion of serotonin, prostaglandins, and other biologically active substances. Cardiac manifestations constitute carcinoid heart disease.Carcinoid Tumors and Syndrome: constellation of symptoms associated with a hormone-producing carcinoid tumorTumorInflammation. Presentation commonly includes flushing, diarrheaDiarrheaDiarrhea is defined as ≥ 3 watery or loose stools in a 24-hour period. There are a multitude of etiologies, which can be classified based on the underlying mechanism of disease. The duration of symptoms (acute or chronic) and characteristics of the stools (e.g., watery, bloody, steatorrheic, mucoid) can help guide further diagnostic evaluation. Diarrhea, and asthma-like symptoms. Carcinoid syndromeCarcinoid syndromeA symptom complex associated with carcinoid tumor and characterized by attacks of severe flushing of the skin, diarrheal watery stools, bronchoconstriction, sudden drops in blood pressure, edema, and ascites. The carcinoid tumors are usually located in the gastrointestinal tract and metastasize to the liver. Symptoms are caused by tumor secretion of serotonin, prostaglandins, and other biologically active substances. Cardiac manifestations constitute carcinoid heart disease.Carcinoid Tumors and Syndrome is usually caused by the secretionSecretionCoagulation Studies of serotoninSerotoninA biochemical messenger and regulator, synthesized from the essential amino acid l-tryptophan. In humans it is found primarily in the central nervous system, gastrointestinal tract, and blood platelets. Serotonin mediates several important physiological functions including neurotransmission, gastrointestinal motility, hemostasis, and cardiovascular integrity.Receptors and Neurotransmitters of the CNS. The diagnosis is established by urinary 5-hydroxyindoleacetic acid (5-HIAA) levels.
InsulinomaInsulinomaA benign tumor of the pancreatic beta cells. Insulinoma secretes excess insulin resulting in hypoglycemia.Pancreatic Neuroendocrine Tumors (PanNETs): an insulin-secreting tumorTumorInflammation. Presentation commonly includes symptoms of hypoglycemiaHypoglycemiaHypoglycemia is an emergency condition defined as a serum glucose level ≤ 70 mg/dL (≤ 3.9 mmol/L) in diabetic patients. In nondiabetic patients, there is no specific or defined limit for normal serum glucose levels, and hypoglycemia is defined mainly by its clinical features. Hypoglycemia such as weakness, confusion, and palpitationsPalpitationsEbstein’s Anomaly. The diagnosis is suspected based on low blood glucoseLow blood glucoseHypoglycemia is an emergency condition defined as a serum glucose level ≤ 70 mg/dl (≤ 3. 9 mmol/l) in diabetic patients. In nondiabetic patients, there is no specific or defined limit for normal serum glucose levels, and hypoglycemia is defined mainly by its clinical features.Hypoglycemia levels associated with symptoms.
Paroxysmal supraventricular tachycardiaTachycardiaAbnormally rapid heartbeat, usually with a heart rate above 100 beats per minute for adults. Tachycardia accompanied by disturbance in the cardiac depolarization (cardiac arrhythmia) is called tachyarrhythmia.Sepsis in Children: episodic condition with abrupt onset of tachyarrhythmiaTachyarrhythmiaA tachyarrhythmia is a rapid heart rhythm, regular or irregular, with a rate > 100 beats/min. Tachyarrhythmia may or may not be accompanied by symptoms of hemodynamic change.Tachyarrhythmias. Paroxysmal supraventricular tachycardiaTachycardiaAbnormally rapid heartbeat, usually with a heart rate above 100 beats per minute for adults. Tachycardia accompanied by disturbance in the cardiac depolarization (cardiac arrhythmia) is called tachyarrhythmia.Sepsis in Children is caused by cardiac conduction abnormalities. Presentation can include palpitationsPalpitationsEbstein’s Anomaly and associated anxietyAnxietyFeelings or emotions of dread, apprehension, and impending disaster but not disabling as with anxiety disorders.Generalized Anxiety Disorder. The diagnosis is established by electrophysiological studies.
Munchausen’s syndrome: psychiatric disorder in which patientsPatientsIndividuals participating in the health care system for the purpose of receiving therapeutic, diagnostic, or preventive procedures.Clinician–Patient Relationship deliberately falsify symptoms of illness. Symptoms can be induced by medication ingestion. The diagnosis may be challenging and requires detailed medical and psychosocial history.
Billing and Coding
Diagnosis Codes:
These codes are used to diagnose a pheochromocytomaPheochromocytomaPheochromocytoma is a catecholamine-secreting tumor derived from chromaffin cells. The majority of tumors originate in the adrenal medulla, but they may also arise from sympathetic ganglia (also referred to as paraganglioma). Symptoms are associated with excessive catecholamine production and commonly include hypertension, tachycardia, headache, and sweating. Pheochromocytoma, a rare tumorTumorInflammation of the adrenal medullaAdrenal MedullaThe inner portion of the adrenal gland. Derived from ectoderm, adrenal medulla consists mainly of chromaffin cells that produces and stores a number of neurotransmitters, mainly adrenaline (epinephrine) and norepinephrine. The activity of the adrenal medulla is regulated by the sympathetic nervous system.Adrenal Glands: Anatomy that secretes excess catecholaminesCatecholaminesA general class of ortho-dihydroxyphenylalkylamines derived from tyrosine.Adrenal Hormones. The codes distinguish between benignBenignFibroadenoma and malignant tumors.
These codes are for the biochemical tests used to diagnose a pheochromocytomaPheochromocytomaPheochromocytoma is a catecholamine-secreting tumor derived from chromaffin cells. The majority of tumors originate in the adrenal medulla, but they may also arise from sympathetic ganglia (also referred to as paraganglioma). Symptoms are associated with excessive catecholamine production and commonly include hypertension, tachycardia, headache, and sweating. Pheochromocytoma, which involve measuring metanephrines and catecholaminesCatecholaminesA general class of ortho-dihydroxyphenylalkylamines derived from tyrosine.Adrenal Hormones in either the plasmaPlasmaThe residual portion of blood that is left after removal of blood cells by centrifugation without prior blood coagulation.Transfusion Products or a 24-hour urine collection.
Coding System
Code
Description
CPT
83835
Metanephrines
CPT
82384
CatecholaminesCatecholaminesA general class of ortho-dihydroxyphenylalkylamines derived from tyrosine.Adrenal Hormones; total, urine
Procedures/Interventions:
This code is for an adrenalectomyAdrenalectomyExcision of one or both adrenal glands.Cushing Syndrome, the surgical removal of the adrenal gland containing the tumorTumorInflammation, which is the definitive treatment for pheochromocytomaPheochromocytomaPheochromocytoma is a catecholamine-secreting tumor derived from chromaffin cells. The majority of tumors originate in the adrenal medulla, but they may also arise from sympathetic ganglia (also referred to as paraganglioma). Symptoms are associated with excessive catecholamine production and commonly include hypertension, tachycardia, headache, and sweating. Pheochromocytoma.
Coding System
Code
Description
CPT
60540
AdrenalectomyAdrenalectomyExcision of one or both adrenal glands.Cushing Syndrome, partial or complete, or exploration of adrenal gland with or without biopsyBiopsyRemoval and pathologic examination of specimens from the living body.Ewing Sarcoma; transabdominal, lumbar or dorsal
Lenders, J., Duh, Q., Eisenhofer, G. et al. (2014). Pheochromocytoma and paraganglioma: an Endocrine Society clinical practice guideline. Journal of Clinical Endocrinology & Metabolism, 99(6), 1915–1942. https://academic.oup.com/jcem/article/99/6/1915/2537399?login=false
The NGS in PPLG Study Group. (2017). Consensus statement on next-generation sequencing-based diagnostic testing of hereditary phaeochromocytomas and paragangliomas. Nature Reviews: Endocrinology, 13, 233–247. https://www.nature.com/articles/nrendo.2016.185.pdf
Taieb, D., et al. (2019). European Association of Nuclear Medicine Practice Guideline/Society of Nuclear Medicine and Molecular Imaging Procedure Standard 2019 for radionuclide imaging of phaeochromocytoma and paraganglioma. European Journal of Nuclear Medicine and Molecular Imaging, 46, 2112–2137. https://link.springer.com/article/10.1007/s00259-019-04398-1
Nolting, S., et al. (2019). Current management of pheochromocytoma/paraganglioma: a guide for the practicing clinician in the era of precision medicine. Cancers, 11(10), 1505. https://www.mdpi.com/2072-6694/11/10/1505
Scheuba, A., Kulterer, O. C., Lehner, R., Rybiczka-Tešulov, M., Esterbauer, H., & Raber, W. (2025). Metastatic Pheochromocytoma/Paraganglioma: Diagnostic Performance of Functional Imaging (18F-Fluoro-L-DOPA-, 68Ga-DOTA- and 18F-Fluoro-Deoxyglucose-Based PET/CT) and of 123I-MIBG Scintigraphy in 57 Patients and 527 Controls During Long-Term Follow-Up. Cancers, 17(23), 3855. https://doi.org/10.3390/cancers17233855
Ebbehoj, A., Iversen, P., Kramer, S., Stochholm, K., Poulsen, P. L., Hjorthaug, K., & Søndergaard, E. (2025). Positron Emission Tomography Imaging of Pheochromocytoma and Paraganglioma-18F-FDOPA vs Somatostatin Analogues. The Journal of clinical endocrinology and metabolism, 110(2), 303–316. https://doi.org/10.1210/clinem/dgae764
Pan, Z., Wang, C., Liu, Q., Xu, X., Wang, Y., Cheng, K., Li, Z., Chen, J., Li, M., & Xiao, Q. (2026). Preoperative Preparation With Selective versus Nonselective Alpha-Adrenoceptor Blockade for Pheochromocytomas and Paragangliomas: A Systematic Review and Updated Meta-Analysis. Endocrine practice : official journal of the American College of Endocrinology and the American Association of Clinical Endocrinologists, S1530-891X(26)00975-4. Advance online publication. https://doi.org/10.1016/j.eprac.2026.05.007
Create your free account or log in to continue reading!